Inside the Abortion Pill: How mifepristone and Misoprostol Transform Care
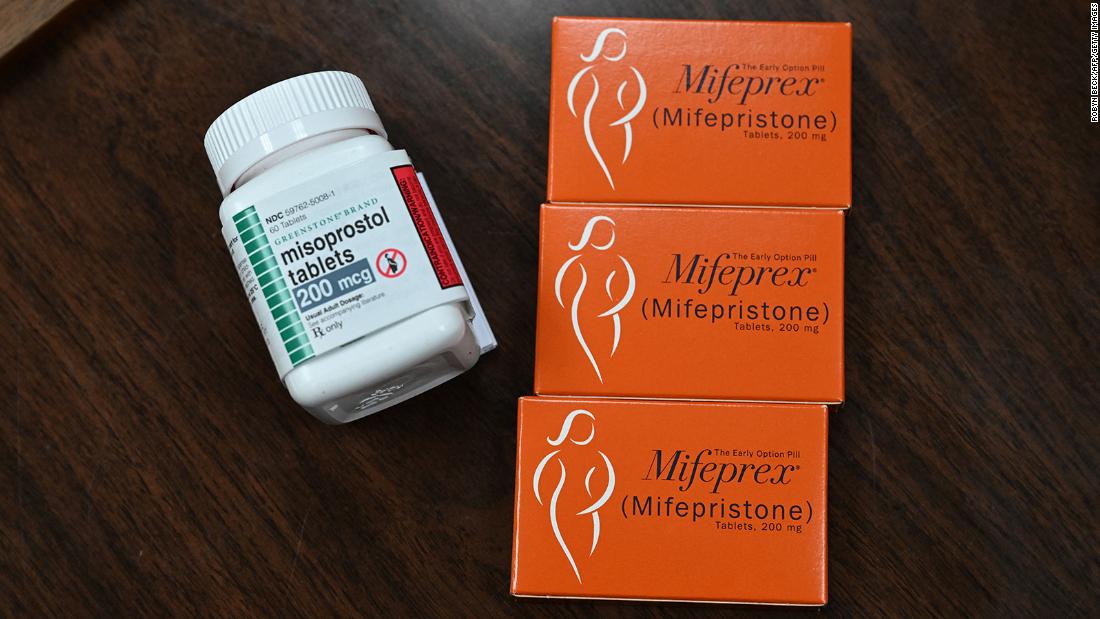
The clinic hallway hums with a new kind of urgency: a patient has just received a prescription for the so‑called abortion pill, and a seasoned physician is poised to demystify the process. Dr. Elena Ramirez, a board‑certified OB‑GYN at a major academic medical center, says the regimen’s two‑step chemistry—first **mifepristone**, then **misoprostol**—offers a clinically proven, outpatient alternative to surgical termination. “The first tablet blocks progesterone, essentially pausing the pregnancy, while the second induces uterine contractions to expel the tissue,” she explains. For patients, the protocol translates into a discreet, cost‑effective option that can be managed at home, reshaping the traditional healthcare delivery model.
At the macro level, the surge in medication abortion reflects broader shifts in reproductive autonomy, telehealth adoption, and regulatory recalibration. Since the **World Health Organization** endorsed the regimen in 2001, a coalition of advocacy groups, including the **Guttmacher Institute**, has lobbied for wider accessibility. The 2021 **FDA** decision to lift the in‑person dispensing requirement—later expanded to over‑the‑counter status in 2023—has catalyzed a cascade of state‑level legal battles. These dynamics intersect with the larger wellness economy, where preventive care and patient‑centered therapies increasingly dominate investment narratives.
Quantitatively, the impact is striking. The **U.S. healthcare market** now records roughly **62%** of all abortions performed via medication, up from 45% a decade ago, according to recent CDC data. This shift translates into an estimated **$1.2 billion** annual revenue stream for manufacturers of **mifepristone** and **misoprostol**, with projected compound annual growth of 7% through 2030. Moreover, a 2022 study published in *The Lancet* found a 98% efficacy rate for pregnancies up to 10 weeks, reinforcing the therapy’s clinical credibility. The cost differential is equally compelling: a full surgical procedure can exceed **$800**, whereas the pill regimen averages **$500**, a margin that influences both patient choice and insurer reimbursement strategies.
From a market perspective, pharmaceutical firms stand to gain from expanded distribution channels, including pharmacies, telemedicine platforms, and even retail giants. Companies such as **Danco Laboratories**, the sole U.S. **FDA**‑approved **mifepristone** manufacturer, have reported a 30% uptick in quarterly sales since the regulatory easing. Yet the upside is tempered by political volatility; state legislatures in 12 jurisdictions have enacted bans or severe restrictions, threatening supply chain continuity and prompting some investors to demand risk‑adjusted pricing. Meanwhile, insurers are recalibrating coverage policies, with several major health plans now classifying the pill as a **therapy** rather than an elective procedure, potentially lowering out‑of‑pocket costs and expanding utilization.
Looking ahead, the strategic horizon hinges on three variables: federal legislation, judicial rulings, and the evolution of telehealth infrastructure. The pending **Supreme Court** case on the constitutionality of state‑level abortion bans could either cement a fragmented market or reopen pathways for uniform national standards. Simultaneously, the rollout of a **diagnosis**‑linked digital platform—integrating home pregnancy tests with e‑prescribing—could accelerate adoption, especially in underserved regions. Stakeholders should also watch for potential **vaccine**‑style public‑health campaigns that frame medication abortion as a preventive **wellness** tool, a narrative shift that could reshape both public perception and funding models.
In this crucible of clinical science, regulatory flux, and market opportunity, the medication abortion story underscores how a single therapeutic duo can reverberate across health policy, investor portfolios, and patient autonomy. As Dr. Ramirez cautions, “The science is settled; the battle now is over how society chooses to integrate it into the fabric of care.”
© Kavam News 2026. All rights reserved.